Concept Bottleneck Models as Decision Support
A radiologist in a public hospital gets a second opinion from a model that flags a shadow on a lung scan, but the model does not stop at the flag. It names the three visual features that drove the call — the irregular margin, the density gradient, the asymmetry against the opposite lung — and the radiologist can accept, reject, or interrogate each one. That is the difference between a system that replaces judgment and one that sharpens it. The same technology, deployed without those named features, becomes a black box that a busy clinician either trusts blindly or ignores. The tool is identical. The design choice is not. This is where automation either deepens the gap between experts and everyone else, or closes it.
The promise and the mechanism
Concept bottleneck models are built on a simple architectural bet: force the AI to reason through human-understandable concepts before it reaches a decision. Instead of mapping pixels directly to “malignant,” the model first predicts intermediate features — “spiculated margin,” “pleural retraction,” “nodule size” — and then combines those into a diagnosis. The bottleneck is literal. Information must pass through the concepts. The appeal is that a person can inspect the reasoning, not just the verdict.
The idea has circulated for years, but the evidence that it actually helps people make better decisions has been thinner than the enthusiasm. A 2026 paper by Alessandro Bogani and five co-authors asks the uncomfortable question directly: are these models effective as decision-support systems? [1] Not as benchmarks, not as accuracy scores, but as tools that a human being uses in a real workflow. The distinction matters because a model can be accurate and still be useless if the person on the other end cannot act on what it says.
What the research actually shows
The study sits in the human-computer interaction space, which means it cares about the person, not just the prediction. That framing is rare. Most work on interpretable AI measures whether the explanation matches the model’s internal logic — a property called faithfulness — and stops there. Faithfulness is necessary but not sufficient. An explanation can be perfectly faithful and still be incomprehensible, or comprehensible and still not change what anyone does.
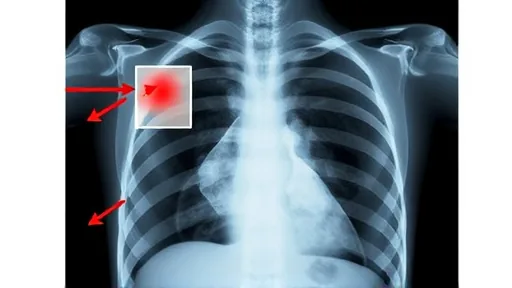
What the researchers probe is the gap between explanation and action. A concept bottleneck model might tell a clinician that “texture irregularity” drove a classification. If the clinician does not know how to verify texture irregularity, or if verifying it takes longer than the original task, the explanation adds cost without adding value. The bottleneck becomes a bottleneck in the worst sense — a constraint that slows the system down without improving the outcome.
This is not a failure of the concept. It is a failure of the assumption that interpretability automatically translates into usefulness. The paper treats that assumption as a hypothesis to test rather than a premise to accept, which is the right posture for a field that has spent a decade celebrating explanations without checking whether anyone benefits from them.
Where the gain is real
The places where concept bottlenecks genuinely lift performance share a pattern. The concepts are ones the human already uses. The verification is fast. The model’s confidence is calibrated enough that the human knows when to look harder. In those conditions, the AI does something a second human colleague cannot always do: it holds a consistent standard across thousands of cases, never gets tired, and never skips a feature because the waiting room is full.
That is a concrete gain, and it is worth stating plainly. Not “AI revolutionizes medicine.” Not “AI replaces doctors.” The gain is narrower and more durable: a system that surfaces the right features at the right moment, so a trained person can make a faster and better-informed call. The lift comes from the interaction, not from the model alone. Remove the human and the concepts become noise. Remove the concepts and the human is back to guessing.
The same logic extends beyond radiology. Any domain where experts reason through named intermediate features — loan underwriting, structural inspection, legal review — is a candidate. The requirement is not a fancy model. It is a model whose reasoning can be checked by the person who bears the consequence of being wrong.
The distance between paper and practice
The paper’s contribution is not a new architecture. It is a measurement of how far the deployed reality sits from the design ideal. Concept bottleneck models are often evaluated in controlled settings where participants are told which concepts to attend to and given time to do so. Real clinics, real loan offices, real inspection sites do not work that way. Time is compressed. Attention is fragmented. The concept list may not match the vocabulary the expert actually uses.
That gap is where the promise either survives or dies. A model that performs well in a study but demands a workflow change no one has time to make will not lift anyone. The research landscape now has enough papers on interpretability to fill a library, and still very few that follow a tool into the room where the decision gets made. The Bogani paper is one of the few that walks that far
The paper is not a verdict on concept bottlenecks. It is a reminder that the interesting question was never whether AI can explain itself. It is whether the explanation arrives in a form, at a speed, and in a vocabulary that lets a person do something they could not do before. That is the only gain that counts, and it is the one most easily lost between the demo and the deployment.